

Understanding hepatitis C
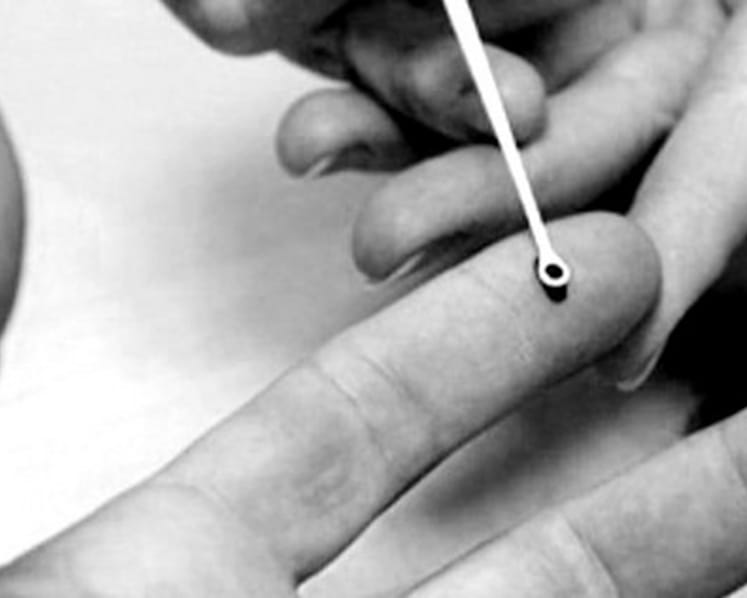
A person being tested for hepatitis C. As the disease is uncommon, most patients and even doctors may not consider it as there are generally no symptoms until advanced liver damage has occurred. Photo: Channel NewsAsia
Singaporeans and healthcare workers here were understandably shocked at the hepatitis C outbreak at Singapore General Hospital (SGH). As a hepatologist, I wish to share the difficulties in detecting and managing the outbreak.
Hepatitis C affects approximately 130 to 210 million individuals worldwide. It is particularly common in Egypt, Mongolia and Pakistan, with up to 20 per cent prevalence in certain regions within these three countries. Possible reasons include the use of contaminated medical equipment and injection needles in poorly funded healthcare systems, and the practice of blood selling, or paid blood donations in these countries.
Fortunately, hepatitis C is rare in Singapore, with less than 1 per cent of the population affected.
Hepatitis C is transmitted through contaminated blood via tattooing, body piercing, acupuncture and injections with contaminated needles. It is generally not transmitted via sexual intercourse, and the risk of sexual transmission is less than 5 per cent among spouses.



In Singapore, we are fortunate that our blood bank is effective and diligent in the screening of blood donors and blood products. Our healthcare systems, public and private alike, also exercise high infection-control standards, so the risk of transmission is low.
HOW DIFFICULT IS THE DIAGNOSIS OF HEP C?
Diagnosis requires a high index of suspicion. As hepatitis C is uncommon, most patients, and even doctors, may not think about the disease as there are generally no symptoms until advanced liver damage has occurred.
A simple screening test is the anti-hepatitis C antibody (anti-HCV) test. It is sensitive, so those who test negative are highly unlikely to be infected with the hepatitis C virus.
But anti-HCV is non-specific — a positive test does not necessarily mean real infection. That can only be confirmed by testing hepatitis C viral load in the blood. I have seen many patients with positive anti-HCV, but negative HCV viral load in blood. Hepatologists label them as “false positive” results. This is thought to be cross-reactivity of other infections with hepatitis C and does not equate an active infection.
Differentiating acute and chronic hepatitis C is difficult. While acute hepatitis C is a new infection, chronic hepatitis C implies the infection has been present for more than six months. In acute cases, patients should have been exposed to blood/contaminants within the past six months, and have had a documented negative anti-HCV test in the past. When these two are difficult to ascertain, doctors tend to label the infection as chronic hepatitis C.
Current Health Ministry guidelines require doctors to only report acute viral hepatitis cases within 72 hours, not chronic cases.
In the SGH outbreak, the 22 cases of acute hepatitis C virus infections were in patients with kidney disease.
It is particularly difficult to manage hepatitis C in patients with renal diseases. First, making a diagnosis is not straightforward in renal failure patients, as their immune system is weaker and anti-HCV may be falsely negative.
Antiviral treatment is another issue. The current treatment for hepatitis C are the Direct Antiviral Agents (DAAs), which offer a more than 90 per cent chance of a cure.
But to date, most DAAs are not well tested in renal failure or post-kidney-transplant patients. We often have to fall back on the old treatment: An injection called pegylated interferon.
In my experience of treating renal failure hepatitis C patients with pegylated interferon, I found them having more adverse effects than patients with normal renal function. Renal patients tend to be more lethargic, complain of more body aches and register a bigger drop in blood counts during treatment.
Treating post-renal-transplant patients could also lead to rejection of the transplanted kidney in up to 50 per cent of patients.
OUTBREAKS WITHIN A MEDICAL FACILITY
According to the United States Centers for Disease Control and Prevention (CDC), there were 22 hepatitis C outbreaks in America from 2008 to 2014, resulting in at least 239 acute hepatitis C cases.
Extensive investigations show that these outbreaks were because of the following factors: 1) The inappropriate sterilisation of medical equipment; 2) The reuse of disposable sharp instruments; 3) A failure to separate and clean contaminated equipment in storage; 4) The preparation of injection medication in the same area where blood specimens are processed; and 5) The transmission of viruses from infected healthcare workers.
In general, the prevention of an outbreak can be grouped in three areas.
First, there must be robust infectious control measures and protocols. At Mount Elizabeth Novena Hospital where I practise, stringent infection control measures include: Medications, oral or injectables must be served by two nurses, who check each other to avoid mistakes; multi-dose vials are limited to one patient per vial to avoid cross-contamination; and all surface areas on cabinets and dialysis machines are thoroughly disinfected before the next patient.
Second, there must be regular and surprise audits. Protocols are only effective if they are followed. Most hospitals have dedicated clinical audit teams who go around conducting regular as well as unannounced audits. The audit team is more interested in helping us to be compliant, rather than punishing non-compliant workers. Hospitals view audits very seriously to ensure all healthcare workers keep the hospital safe.
Third, healthcare workers have to be vigilant and meticulous. They deal with the lives and health of patients, and must follow instructions diligently and meticulously. Taking shortcuts puts patients and healthcare workers at risk. Hospital administrators must also make it easy for healthcare workers to be compliant. Some processes include having nurses who serve medications put on a “Do Not Disturb” apron so they can focus on checking and serving the medicine. Biohazard sharps boxes, disinfectant handwash and washbasins should be conveniently located in many parts of the wards.
The Independent Review Committee tasked by the Ministry of Health to look at how SGH handled the hepatitis C outbreak will look into processes at both SGH and MOH to identify whether there are any gaps and areas that can be improved upon.
Conducting retrospective audits and investigations is never easy. In the US, despite extensive investigations, the final cause of hepatitis C outbreaks could not be identified in some instances. But it is important to find ways to improve compliance to protocols.
With strict infection-control measures, a strong adherence to protocols and having meticulous healthcare workers, we can minimise future hospital outbreaks of infectious diseases. While awaiting the verdict of the Independent Review Committee, we ought to continue to show support to all our healthcare workers.
ABOUT THE AUTHOR:
Dr Desmond Wai is a gastroenterologist and hepatologist in private practice.




